DOME | Maxillary Expansion for
Sleep-Disordered Breathing
Maxillary morphology, particularly in the transverse dimension, has a profound impact on all aspects of Sleep-Disordered Breathing (SDB)

The demands on nasal breathing differs between wakefulness and sleep.
Anatomic causes of nasal obstruction often include structures of the internal nasal valve - the septum, the inferior turbinates, and the upper lateral cartilages. Often times, we are successful in treating nasal obstruction surgically with focus in these structures.
What happens when patients do not respond as well after “intra-nasal” procedures such as septoplasty and inferior turbinate reduction?
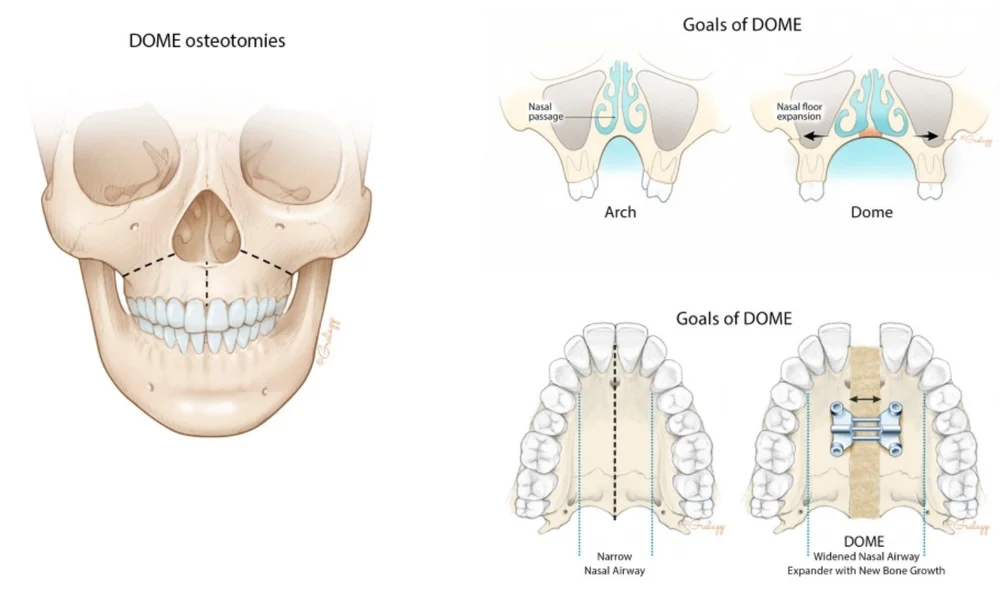
The cross-sectional area of the internal nasal valve is significantly influenced by the width of the nasal floor. The nasal floor is also the roof of the maxilla (upper jaw).
For patients with sleep-disordered breathing (including upper airway resistance syndrome and obstructive sleep apnea), a narrow nasal floor means
1) More resistance to nasal breathing during sleep
2) Less room for the tongue, leading to posterior tongue displacement (obstructs airway). Posterior displacement of the tongue can also push against the soft palate during sleep, which further exacerbates the problem.
In that situation, expansion of the nasal floor via the maxillary floor/palatal roof becomes an option.
This slows airflow through the nasal passages, which lessens the negative pressure that collapses the pharyngeal airway.
Expansion of the nasal passages means more nasal mucosa, which is responsible for the benefits to nasal breathing.
In 2015, when Dr. Liu first started addressing this anatomic phenotype at Stanford with Dr. Christian Guilleminault and Dr. Audrey Yoon, he found himself explaining to patients that the aim is to transform the “narrow, high-arch” palate to a “dome” shaped palate.
Over time, we decided to describe the process as “DOME - Distraction Osteogenesis with Maxillary Expansion.” It is easy to understand, as we create a dome-shaped palatal roof. Furthermore, we aim to grow bone via distraction (hence distraction osteogenesis), at the nasal floor, during transverse maxillary expansion.
DOME has since evolved significantly in all areas.
More specific patient phenotyping
Custom expander designs
Less invasive, or elimination, of osteotomies
Improved esthetic and periodontal processes
Many orthodontists and surgeons have since developed their own approaches to naso-maxillary expansion, for the treatment of patients with sleep-disordered breathing and transverse maxillary hypoplasia (narrow upper jaw).
“I envision that we will all continue to improve patient-specific methods to creating the ‘dome’ shaped palate, to promote nasal breathing during sleep,” says Dr. Liu. “Our common goals are to alleviate severity of sleep-disordered breathing, nasal obstruction, and daytime sleepiness.”
Most adults go through DOME without major problems. In Dr. Liu's published series of 32 adults, there was no infection, opening between the mouth and nose, sinusitis, loss of a front tooth or problem with bone healing. We review your own risks with you before treatment.
- Pain and swelling
- Expected for the first few days, mostly around the upper lip and nose.
- Gap between the front teeth
- A gap opens between the upper front teeth as the upper jaw widens. It shows the expansion is working, and orthodontic treatment closes it.
- Numbness
- The upper front teeth, gums or palate may feel numb. This usually improves over weeks to months.
- Uneven expansion
- One side can widen more than the other. In the published series this happened in 2 of 32 patients.
- Gums and teeth
- Gum recession or tooth sensitivity can develop near the front teeth. Healthy gums are needed before DOME, so a gum check comes first.
- Expander problems
- The expander or its small anchor screws can loosen or irritate the palate, and may need adjustment.
- Nosebleed
- Minor bleeding from the nose is possible in the first days.
- Infection
- Uncommon, and treated with antibiotics when it happens.
- Your part
- Turning the expander as instructed, then orthodontic treatment, are part of the plan. The result depends on both.
- Anesthesia
- Risks of general anesthesia are reviewed with you by the anesthesia team.
DOMEzero
Skeletal-only Expander with No Diastema using Synchronized Clear Aligner Alignment
Credit to Dr. Claudia Pinter and Dr. Christian Leonhardt
Classically, there is a period during and after maxillary expansion, where a significant gap develops between the maxillary incisors (front teeth of the upper jaw). Some doctors and patients like this gap (“diastema”), while others wish to avoid it.
My colleagues in Vienna and Germany showcased their work, which we will call DOMEzero that avoids the gap. This is achieved by close coordination between maxillary expansion (with custom expanders), and clear aligners (for orthodontic movement). Hence, while the jaw bone and nasal floor are being expanded, the teeth (and bite) are restored concurrently.
DOME: Past, Present, and Precision
How an operation for one anatomic phenotype, the adult narrow maxilla with a high-arched palate, became a line of research and a shared protocol.

A phenotype without an operation
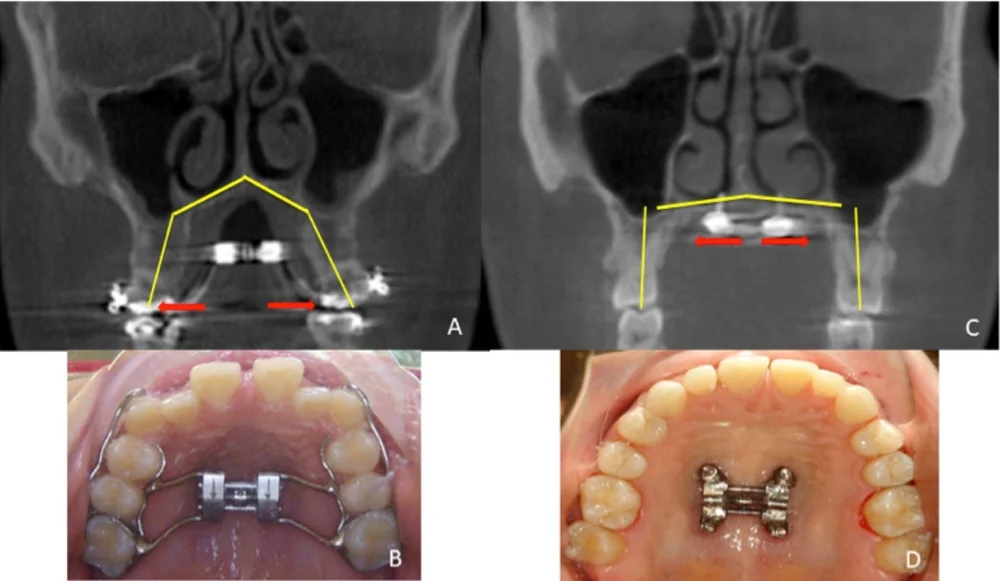
Dental expanders exert force at the maxillary molars, which does not reliably widen the nasal floor along the midpalatal region, and tooth-borne surgically assisted expansion has a relapse rate reported as high as 64%. The adult with a narrow, high-arched palate, normal occlusion, and intolerance of CPAP had no operation designed for this phenotype.
At Stanford, with Dr. Christian Guilleminault and Dr. Audrey Yoon, we anchored a custom expander to the palate on four to six mini-implants, released the maxilla with a limited Le Fort I osteotomy, and distracted the midpalatal suture to grow bone at the nasal floor.
- 2014 to 2016First 20 adults treated at Stanford.
- 2016First international presentation, IPSA, Taipei, with Dr. Audrey Yoon.
- 2017Technique and first results published: AHI 30.9 to 14.2, NOSE 11.7 to 3.85. Presented at World Sleep, Prague.
From the palate to the nasal valve
The question moved from whether DOME widens the palate to what that widening does for breathing. In 75 adults, the AHI fell from 17.65 to 8.17 and nasal obstruction (NOSE) from 10.94 to 3.28, with no major complications. Patient-specific airflow models showed why: nasal airflow velocity fell by half and negative pressure in the pharynx fell about threefold, while the dimensions of the pharynx did not change.
- 2019The internal nasal valve widens after DOME. In the narrow maxilla, DOME is offered before septoplasty and turbinate surgery.
- 2020The 75-patient series and the airflow mechanism (nasal velocity 15.59 to 7.41 m/s).
- 2022DOME after failed septoplasty: nasal floor 22.4 to 28.06 mm. MINE-DOME moves the osteotomies to an endoscopic, transnasal approach.
- TodayThe protocol is taught to surgeons and orthodontists in Vienna, with Dr. Claudia Pinter.


Skeletal expansion and alignment on one timeline
Of every skeletal, dental, and airway change we measured after DOME, only widening of the nasal floor at the nasopalatine canal correlated strongly with the reduction in AHI. Hence, the next question is not whether to expand, but where, and how to get there with less disruption to the patient.
DOMEzero coordinates bone-anchored maxillary expansion with clear aligner orthodontics. The expansion and the orthodontics are digitally designed to happen at the same time, rather than as separate or sequential treatments, and every case is planned by the DOME orthodontic team headed by Dr. Claudia Pinter. The goal is a larger palate, a larger nasal airway, and more tongue space, with a stable, esthetic bite and without bicuspid extraction.
However, candidacy and outcomes vary with anatomy, and the surgical DOME remains available when the anatomy requires definitive surgical separation. Precision follows the same triad as the rest of sleep surgery: (1) patient selection, (2) procedural selection, and (3) procedural accuracy.
- One timelineThe skeleton widens while the teeth track, with no months-long wait between the expansion and orthodontic phases.
- No gapThe central diastema that classically opens during expansion never forms.
- ProtocolA bandless, custom expander placed screws-first, synchronized aligners, myofunctional therapy, release of tethered oral tissues, and a neutral bite.
- Nov 2026DOME Summit, Clearwater Beach, November 6 and 7: the first convening of the integrated sleep, breathing, and modern orthodontics network.
References (7)
- Liu SY-C, Guilleminault C, Huon L-K, Yoon A. Distraction osteogenesis maxillary expansion (DOME) for adult obstructive sleep apnea patients with high arched palate. Otolaryngol Head Neck Surg. 2017;157(2):345-348.
- Abdelwahab M, Yoon A, Okland T, Poomkonsarn S, Gouveia C, Liu SY-C. Impact of distraction osteogenesis maxillary expansion on the internal nasal valve in obstructive sleep apnea. Otolaryngol Head Neck Surg. 2019;161(2):362-367.
- Yoon A, Guilleminault C, Zaghi S, Liu SY-C. Distraction osteogenesis maxillary expansion (DOME) for adult obstructive sleep apnea patients with narrow maxilla and nasal floor. Sleep Med. 2020;65:172-176.
- Iwasaki T, Yoon A, Guilleminault C, Yamasaki Y, Liu SY. How does distraction osteogenesis maxillary expansion (DOME) reduce severity of obstructive sleep apnea? Sleep Breath. 2020;24(1):287-296.
- Liu SY-C, Yoon A, Abdelwahab M, Yu MS. Feasibility of distraction osteogenesis maxillary expansion in patients with persistent nasal obstruction after septoplasty. Int Forum Allergy Rhinol. 2022;12(6):868-871.
- Liu SY-C, Ibrahim B, Abdelwahab M, Chou C, Capasso R, Yoon A. A minimally invasive nasal endoscopic approach to distraction osteogenesis maxillary expansion to restore nasal breathing for adults with narrow maxilla. Facial Plast Surg Aesthet Med. 2022;24(6):417-421.
- Yoon A, Kim TK, Abdelwahab M, et al. (Liu SY, senior author). What changes in maxillary morphology from distraction osteogenesis maxillary expansion (DOME) correlate with subjective and objective OSA measures? Sleep Breath. 2023;27:1967-1975.